Contract-aware revenue integrity for hospitals and health systemsEvery finding cites the contractReport-only, your team decidesHIPAA BAA signed before any data moves
Your payer contracts, executed against every claim and every remit
Clinical Speed turns a hospital's payer contracts into an engine that checks its claims from both sides. It proves what the payer owes under the contract, shows what the hospital's own chargemaster costs it, and finds what is missing from the claim and from the care.
Our engineers and contract analysts code every contract, fee schedule and amendment into effective-dated logic, and every finding cites the clause behind it. The platform is report-only, so the hospital's coders, billers and clinicians make every decision.
Report-only, nothing written into your claimsRecovery on contingency, with no setup feeHIPAA BAA signed before any data moves
Revenue Dashboard · UnderpaymentLIVE PLATFORM
Demo Hospital account · payer and patient identifiers blurred
Every findingcites the contract clause, the rate column and the calculation behind it
Report-onlywith no write-back. Your coders, billers and clinicians make every decision
Both sidesof the claim: what the payer owes you and what your own charges cost you
$75M+hospitals to multi-billion-dollar systems, with references offered case by case
The lineup
Three products on one contract engine
Most hospitals start with the Underpayment Audit, because underpayments lead the first conversation and the audit costs nothing up front. That engagement codes the payer contracts and loads the 835 and 837 history, and the same data then shows the hospital its Max Allowable and Encounter Integrity findings.
01Most hospitals start here
Underpayment Audit
“Did the payer pay what the contract says?”
Every 835 remit is priced against the contract in force on its date of service, with the payer's reasons written out in words. Each underpaid line is proven with its clause and recovered by appeal once your team verifies it, and lines paid above the contract go to your compliance office.
12 to 24 months of remits, every line priced
Denials and small balances in the same pass
Clause-cited appeals, worked to a result
Overpayments reported to compliance, date-stamped
Commercial termsContingency-based, with no setup fee. Nothing is owed if nothing is recovered.
“Did our own charge cap what the contract would pay?”
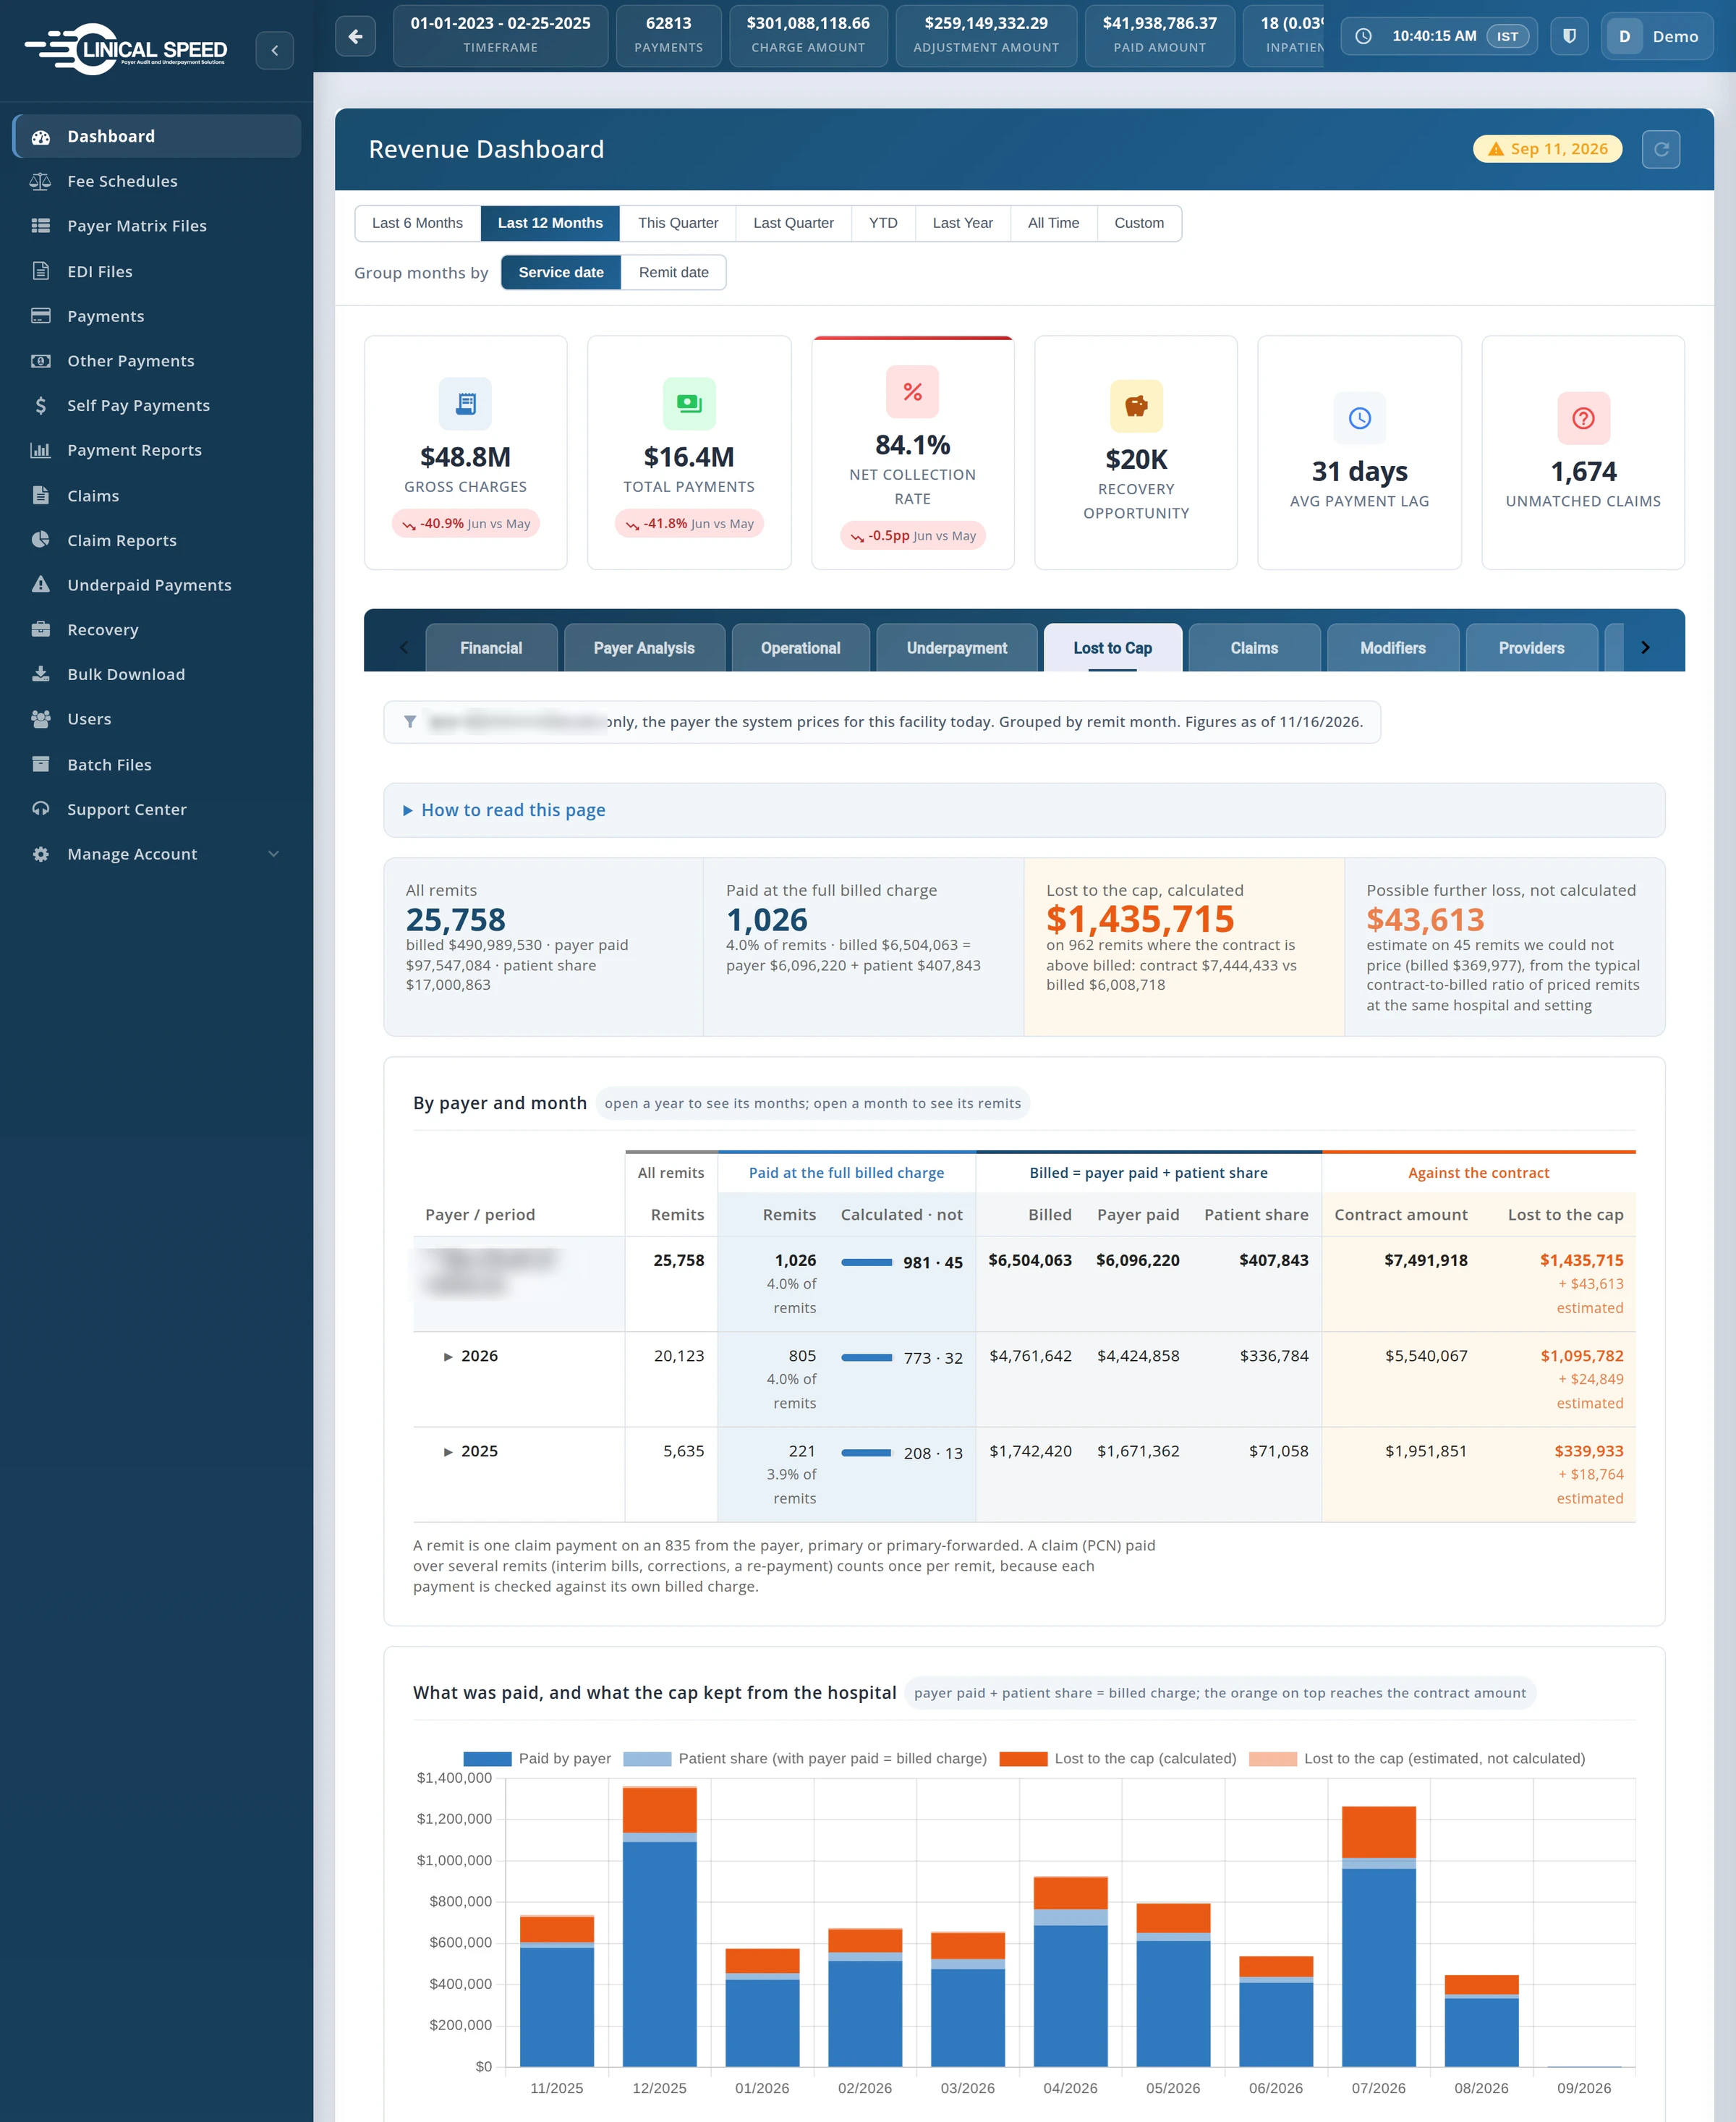
Your chargemaster against your contracts. Lost to Cap measures what lesser-of clauses cost you, remit by remit, and Contract Basis quotes the clause that governs each service line with a compliant rationale for your billing office and CDM committee.
Lost to Cap and Contract Basis views
The governing clause quoted by service line
CDM Repricing Proposal with the all-payer effect
Pre-Submission Contract QA included
Commercial termsA one-time installation and training fee plus contingency, set in the proposal.
“What is missing from the claim and from the care?”
One package in two parts, on the same contract engine and the same claim history. The Missed Charge Audit finds documented services that were never charged. The Care Gap Review sends guideline-cited care gaps to the treating clinician, who decides.
Missed charges and likely over-charges, equal weight
Fixed by late charge or corrected claim
Care gaps cited to published guidelines
The clinician decides every care gap
Commercial termsA one-time installation and training fee plus contingency, set in the proposal.
The Underpayment Audit codes your payer contracts and loads your 835 and 837 history. That same coded policy and claim data then show the Max Allowable and Encounter Integrity findings for your own hospital, before anything new is installed.
Both sides of the claim, from one executable contract
Clinical Speed reviews both sides of a hospital's claim from one executable copy of its contracts. The payer's side is proven line by line on the 835 and appealed once your team verifies it. Your own side, the chargemaster and the claim, is measured against the same contract, and your committee decides every change.
An outpatient surgery visit billed under the HMO plan column of the contract. The contract allows $3,600 for the visit as one case rate. The payer folded the surgery into the implant and drug lines under CARC 97 and paid $900, and the patient owed $250.
Recovered from the payer by appeal, after your team verifies the finding. Our AI writes the contract-cited reasons, thousands an hour, with the clause, rate column and calculation on each line.
Illustrative claim, modelled on a real two-hospital case study
←→
One engine
Your contracts, executed
Our engineers and contract analysts code every value on every page of each payer contract and fee schedule into effective-dated logic, so every remit is priced on the rate sheet in force on its date of service.
Fee schedulesRate columnsDRG and APCModifiersBundlingNCCI pairsMPPRCase ratesPer diemsCarve-outsStop-lossLesser-of termsTimely filing
835After the remit returns: what the payer owes837Your charges and claims: what they cost you
Every finding cites the clause, the fee-schedule cell and the rule that governs the line.
Your side · chargemaster against contract
Max Allowable Audit
A six-day inpatient stay billed under the PPO reciprocity column of the contract. The contract pays a per diem of $4,100 a day, or $24,600 for the stay. The hospital billed $19,900, and the payer paid that charge to the cent under the contract's lesser-of clause.
Stopped going forward through the chargemaster. Your CDM committee adopts one uniform price for every payer, effective on a date, with the all-payer effect shown first.
Illustrative claim, modelled on a real two-hospital case study
The platform
The screens your team works in
Every number on a Clinical Speed screen opens to the remits behind it.
The Resolution Center proves one underpaid claim at a time: the amount owed, the contract, the plan column, the rule and the result, then every line priced against the contract. The Lost to Cap dashboard shows what the hospital's own charges kept from it, by payer and month, remit by remit.
Underpayment Audit
The Resolution Center proves each claim
The amount owed, the contract, the plan column, the rule and the result, then every line priced against the contract with the payer's adjustments written out in words.
Resolution Center · one underpaid claimLIVE PLATFORM
Demo Hospital account · payer and patient identifiers blurred
Max Allowable Audit
Lost to Cap shows what your charges kept from you
Remits paid at the full billed charge, priced against the contract, by payer and month, with the services behind the loss for your chargemaster committee.
Revenue Dashboard · Lost to CapLIVE PLATFORM
Demo Hospital account · payer and patient identifiers blurred
Case study
One client, one payer, twelve months
Clinical Speed audited one commercial payer for a two-hospital health system in California. The engagement coded every contract, fee schedule and program the system holds with that payer and loaded twelve months of 835 and 837 files for both hospitals. The engine matched 45,591 claims to their remittances and found $1.53 million that payer underpaid, across 1,391 claims, each compiled and ready to file. A further $492,877 had already passed that payer's timely-filing deadline, and those claims are documented for the system's legal team. The Max Allowable Audit found more than $4.4 million a year in the client's own charges billed below the contract, about $367,000 a month across 3,600 claims. The payer paid those claims correctly, so the client stops that loss going forward by correcting its chargemaster.
Case study · one client, one payer, twelve months. An example from one client, not a projection. Every hospital's contracts and results differ.
Your team names its owners and payers, and the file request goes out.
024 to 6 weeks
Contracts coded
Each contract is checked with your team, then coded with its dates.
0312 to 24 months
Files loaded
Remits and claims arrive by secure transfer, matched on claim number.
04Under a week
Forensic calculation
Every line is priced against its contract, each variance with its basis.
05Your review
Hospital verification
No appeal file moves until your team has reviewed and approved it.
06Weekly
Appeals and reporting
Verified claims go to appeal, with results after each weekly upload.
60%+of collections typically post within the first 60 days of the recovery cycle, and fees are invoiced only after cash posts to your accounts.
Governance
Report-only, verified and HIPAA-governed
The engine reports and the hospital decides. Coders, HIM and clinicians keep every decision, chargemaster changes are uniform prices for every payer, and no appeal file moves without your verification. A Business Associate Agreement governs all protected health information, which is masked by default and logged on every view.
Claim scrubbers apply generic rule libraries. Contract repositories store terms without pricing claims against them. Late-stage recovery vendors start after the remit returns, and statistical estimators forecast from historical averages. Clinical Speed runs beside each of them from your own executed contracts.
Capability
Clinical Speed
Claim scrubbers
Contract repositories
Late-stage recovery vendors
Statistical estimators
Executes your own contracts, effective-dated, at line level
Every contract
Generic rules
Stores terms
Varies
Averages
Cites the clause behind every finding
Yes
No
Some
Varies
No
Recovers underpayments through appeal
Underpayment Audit
No
No
Yes
No
Measures lesser-of loss on your own charges
Max Allowable Audit
No
No
No
No
Checks the 837 against your contract before it is sent
Contract QA
Generic edits
No
No
Forecast
Finds documented services missing from the claim, priced by contract
Encounter Integrity
Edits only
No
No
No
Reports overpayments to your compliance office
Every engagement
No
No
Varies
No
Categories are described from their published product models. Individual vendors vary, and a demo covers how Clinical Speed sits beside the tools you already run. See the full comparison.
Request a demo
See the platform on your own terms
A demo walks through the de-identified Demo Hospital account, a copy of a real health system's results with every name replaced and the dollar amounts kept. It covers the contract model, the Resolution Center that proves each underpayment, the Lost to Cap and Contract Basis views, Encounter Integrity and the recovery cases with their appeals. Courtney Garner, our Chief Operating Officer, schedules each demo and leads the discovery conversation that follows it.
01The Underpayment Audit and the Max Allowable Audit, screen by screen, from the files sent to the dollars recovered
02Encounter Integrity: the Missed Charge Audit and the Care Gap Review, and who on your team decides each finding
03Your payer mix, your 835 lookback and the contracts, files and access an engagement needs
Courtney GarnerChief Operating Officer, schedules every demo
Clients run from hospitals of about $75M to multi-billion-dollar health systems. References are offered case by case during initial discussions.